
Why Malaysian vet clinics lose hours at the front desk
Most veterinary teams in Malaysia do not struggle because they lack clinical skill. They struggle because the day is chopped into phone callbacks, double-booked wellness slots, and last-minute surgery admits that collide with walk-ins. A clear clinic operations setup for veterinary teams conversation usually starts here: not with a feature list, but with how appointments, records, and stock handoffs actually move through one morning. This article is operational education for clinic managers and lead vets. It is not a product pitch.
Separate appointment types before you open online booking
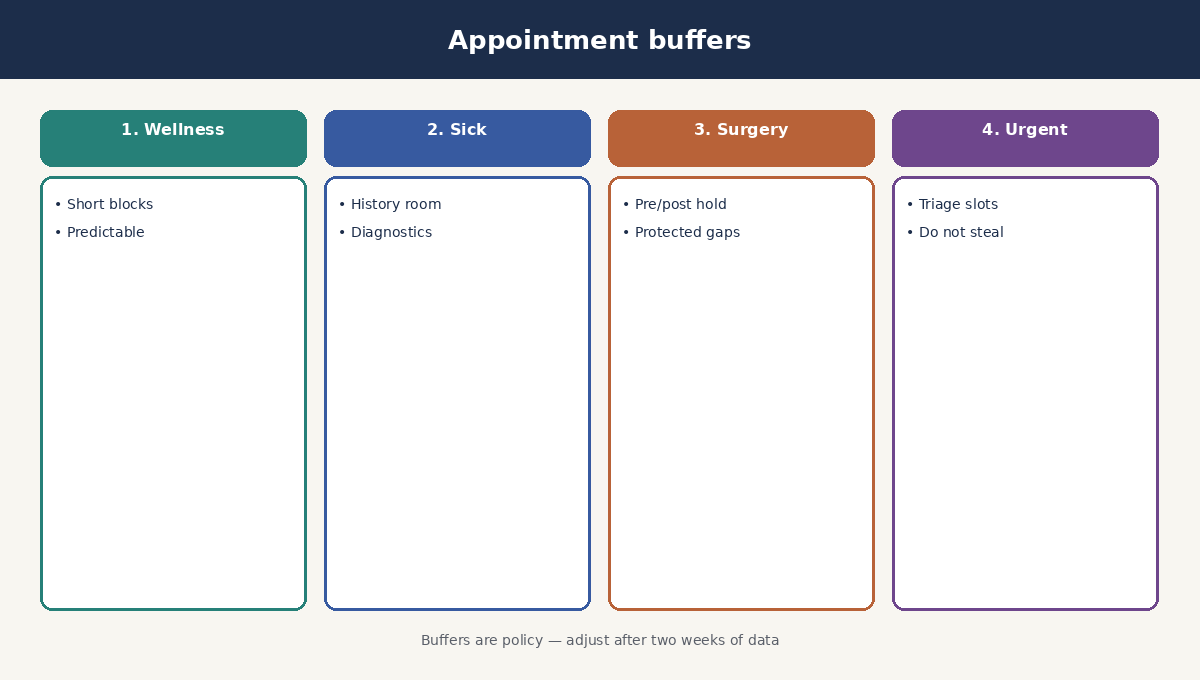
If every request looks the same on the calendar, your buffer times will fail. Wellness and vaccine visits need short, predictable blocks. Sick consults need room for history and diagnostics. Surgery admits need hold time before and after the procedure. Urgent triage should keep protected gaps rather than steal every remaining slot.
Practice-management writers at the American Animal Hospital Association (AAHA) and AVMA practice-management resources keep returning to the same idea: technology helps only when it matches real workflow. Clinics that copy a human salon booking template discover that pets, owners, and inpatient wards do not behave like haircuts. Decide which visit types clients may self-book. Many teams keep complex cases phone-only while allowing routine rechecks online.
When you review veterinary appointment scheduling software, ask dull, specific questions. Can you block surgery days? Can you stop double-booking the only ultrasound room? Can reminders go out without creating a second spreadsheet that nobody owns?

Inventory and records should travel with the consult
Scheduling failures often hide inventory failures. A consult finishes, the script is written, and the dispenser discovers the antibiotic count is wrong. Staff then hunt through paper logs while the next client waits. Accreditation-minded hospitals treat controlled drugs, vaccine cold-chain notes, and who-adjusted-stock logs as clinical quality issues, not back-office trivia.
A workable daily rhythm looks like this: overnight confirmations, a short morning huddle on surgery and inpatients, charge capture in the room, and an end-of-day check on high-velocity items. If your clinic inventory and records overview trail cannot show who changed inventory and when, audits become archaeology.
Multi-branch teams should also decide which stock is site-owned versus transferable. A vaccine moved between clinics without a record creates both clinical risk and ghost inventory. The same logic applies to lab samples and referral paperwork: one incomplete handoff late in the day becomes tomorrow morning’s phone chaos.
Veterinary Business Institute discussion on automation and scheduling efficiency. Educational context; adapt ideas to Malaysian staffing and e-invoice realities.
Malaysia ops notes: e-invoicing and multi-branch reality
Clinics adding a second branch or a mobile service learn quickly that one shared WhatsApp calendar does not scale. You need role-based access, a single patient history, and invoice fields that can support e-invoice workflows as LHDN requirements mature for your entity type. Treat compliance as a scheduling constraint: if invoices cannot close cleanly, reception will keep clients waiting while someone rebuilds a bill.
Also document who may override a booking rule. When every staff member can unlock “just this once” exceptions, your carefully designed buffers collapse by Wednesday.
When you trial a new booking rule, keep a paper shadow calendar for three busy days. Compare no-show rates, overtime minutes, and how often the dispenser had to leave the counter to hunt stock. Those three numbers tell you whether the software change helped the floor, or only cleaned the screen.
A two-week scheduling experiment
Pick one metric for the next fortnight: average phone hold time, same-day rework of appointments, or the share of consults that close with complete charges. Change only one scheduling rule at a time. Keep a short staff note on what broke. Soft planning question for this month: if your busiest vet were on leave for five days, would the calendar still protect surgery and triage, or would every gap fill with hope?